
Aug 3, 2016
Using voice analysis to identify peaks on bipolar disorder is a summary of a recently-published research paper titled “Voice analysis as an objective state marker in bipolar disorder.” For additional information, please click on the link.
The human voice is composed of multiple different components, created through complex muscle movements, making each person’s voice individual, like ‘a fingerprint’. Studies analysing speech in affective disorders, date back as early as 1938. Several clinical observations suggest that changes in speech features have been suggested as valid measures, to identify periods of depression and mania in bipolar disorder. For instance, reduced speech activity may be considered a symptom of depression, and increased speech activity may predict a switch to hypomania.
A pilot study conducted by The Copenhagen Clinic for Affective Disorders, with patients with bipolar disorder, aimed to investigate the following:
- Voice features collected during phone calls, as objective markers of affective states in bipolar disorder
- If combining voice features with automatically generated objective smartphone data on behavioural activities (for example, number of text messages and phone calls per day) and electronic self-monitored data (mood) on illness activity, would increase the accuracy as a marker of affective states
The pilot study included the monitoring of 28 outpatients with bipolar disorder, in a natural environment from October 2013 to December 2014. During this period, patients were given a smartphone application developed by Monsenso, to collect voice features, electronic self-monitoring data, and collection of automatically generated data.
- Voice features
The voice features were extracted from the patients’ phone calls throughout the day, using the open-source Media Interpretation by Large feature-space Extraction (openSMILE) toolkit, which is a feature extractor for signal processing and machine learning applications.
- Electronic self-monitoring data
Patients were requested to provide daily electronic self-monitoring data. The parameters evaluated included: mood, sleep length, medication intake, activity level, alcohol consumption, mixed mood, irritability, cognitive problems, stress levels, and individualised early warning signs.
- Automatically generated data
Through the smartphones’ sensors, automated data tracking different aspects of behavioural activities was collected on a daily basis. The data compiled by the smartphones included the number and duration of phone calls and text messages, accelerometer data, and phone usage.
Results
This innovative study revealed that changes in voice features could, in fact, detect individual changes in affective state. The accuracy of the prediction is increased, by combining voice features with automatically generated smartphone data on behavioural activities, and electronic self-monitoring. Therefore, according to the study, voice features collected by smartphones in a natural setting, could be used as an objective state marker in patients with bipolar disorder.
According to the researchers, the monitoring of symptoms in bipolar disorder and the accurate classification of affective states based exclusively on voice features has great potential.
Clinicians would be able to obtain accurate, objective data in real-time on the patients’ affective states based on collected voice features. The smartphone application could be used to monitor symptoms long-term, outside clinical settings, and enable early intervention between outpatient visits.
According to the researchers, at the time the study was conducted, it was the first study ever that investigated the combinations of voice features; automatically generated data, and electronic self-monitored data as state markers in patients with bipolar disorder. Using feature analysis collected in real-time from smartphones for classifying affective states in bipolar disorder reflects an innovative, objective and unobtrusive method for monitoring of illness activity (state) during long-term and in naturalistic settings.
Reference:
Voice analysis as an objective state marker in bipolar disorder. M. Faurholt-Jepsen, J.Busk, M.Frost, M.Vinberg, E.M.Christensen, O.Winther, J.E.Bardram and L.V.Kessing. 5 May 2016. http://www.nature.com/tp/journal/v6/n7/pdf/tp2016123a.pdf

Jul 5, 2016
Using smartphone apps to improve mental healthcare is definitely a possibility in today’s world where almost everything can be taken care of with just a click.
According to the ECNP/EBC report, there 165 million people or 38% of the population in Europe are affected by a mental illness. The successful treatment of mentally-ill individuals depends on some factors, and medication alone is not sufficient. There are various methods of treatment which they often include a mixture of therapy, self-help, and medication. Some individuals also choose to include exercise, meditation and creative art therapies, to help in their recovery process.
Smartphone apps to improve mental healthcare, an alternative that goes beyond
We live in an era where we have integrated smartphones in our daily lives, from conducting business, to interacting with our loved ones; and from purchasing items online to doing research on something we are interested. Can we take advantage of this technology to help those who need it the most?
It is a well-known fact that there is a major shortage of trained professionals who provide the kind of care patients need. In Europe alone it has been estimated that only 25% of individuals suffering from any mental disorder undergo treatment; while it is also estimated that only 10% of those mentally-ill receive an “adequate treatment.”
There are hundreds of mood trackers and mental health apps available for download. However, they have not been developed with the support from trained clinicians and have no evidence from clinical trials. Is this really the best way to go?
Huge Potential
If thoroughly tested and implemented effectively, mobile health applications can help clinicians and individuals by enabling self-treatment, speeding up the recovery process and prioritising treatment for those who need it the most.
Monsenso is a Copenhagen-based emerging company offering an mHealth platform to help clinicians overcome the burden of mental disorders. The effectiveness of this innovative solution is due to its double-loop treatment model.
On one side, healthcare providers use a web portal to monitor individuals on a continuous basis, identify early-warning signs and offer proactive treatment. On the other, users employ a smartphone to collect data, which is sent automatically to the clinic, enabling healthcare providers to deliver a prompt response.
Clinicians and users can easily access all historical data captured through the smartphone and obtain an accurate analysis and patterns of such data. In additional to historical data, the system can also provide accurate predictions of a patient’s moods and states during the upcoming five days.
Monsenso’s technology is based on continuous research. At the moment, there are ongoing studies and technical trials in bipolar disorder and schizophrenia to ensure the system is stable, scalable and that it helps improve an individual’s well-being.
This is just the beginning
Although mental health care providers deliver a fantastic care, there are hardly enough professionals to ensure everyone receives adequate treatment. Technology and innovation are required to ensure that people living with mental disorders obtain the best treatment available in a timely manner.
Click on the links to learn more about the Monsenso mHealth solution mental health consisting on a smartphone app for individuals, carers and a web portal for clinicians.
Reference:
[1] The size and burden of mental disorders and other disorders of the brain in Europe 2010. ECNP/EBC REPORT 2011.
https://www.ecnp.eu/~/media/Files/ecnp/communication/reports/ECNP%20EBC%20Report.pdf

Jun 21, 2016
According to a recent statement by the new American Heart Association (AHA), major depressive disorder and bipolar disorder should be recognized as moderate risk factors for atherosclerosis and early cardiovascular disease. [1]
In 2011, the National Heart, Lung and Blood Institute identified four conditions (chronic inflammatory disease, human immunodeficiency virus, Kawasaki disease, and nephritic syndrome) that lead youths to a mild risk of developing cardiovascular disease before they reach 30. [2]
The statement released a few days ago, reveals that depression and bipolar disorder meet the same criteria as these conditions. Moreover, these two behavioural disorders are more widespread than the previous mentioned conditions combined.
These studies showed evidence of a link between paediatric depression and bipolar disorder with premature cardiovascular mortality. Cardiovascular risk factors for these teens include obesity, insulin resistance and diabetes, dyslipidemia, and hypertension.[1] According to the statement, depression and bipolar disorder are the first- and fourth-most disabling conditions, among adolescents worldwide.
After the report had been unveiled, researchers from schools around the U.S. and Canada looked at existing studies on mood disorders in people under the age of 30. Researchers looked specifically into youths suffering from depression or bipolar disorder with cardiovascular markers such as high pressure and cholesterol. They found a significant connection between having depression or bipolar disorder and increased odds of high blood pressure, high cholesterol, obesity (especially belly fat), type 2 diabetes, and hardening of the arteries. [3]
This discovery denotes that healthcare providers should track physical activity levels and food intake as well as metabolic monitoring is crucial for these young patients as a preventive measure.
However, to monitor cardiovascular markers, physical activity and food intake, of thousands of young patients who also suffer from mental illness is not an easy task. Although, there are hundreds of smartphone applications tracking physical activity and counting calories, these apps are personal, and clinicians do not have access to an individual’s data. Nevertheless, with the Monsenso mobile health (mHealth) solution, this cumbersome task becomes easy and achievable.
The Monsenso mHealth solution enables clinicians to access a patient’s data on a daily basis. Every day, youths would be reminded to fill in a self-assessment with important information that could include the number of hours they slept, the amount of unhealthy food they have eaten, and if they realized any physical activity throughout their day. Additionally, the smartphone can also collect physical activity and mobility data, based on the smartphone’s inbuilt accelerometer and GPS locator.
The Monsenso mHealth solution, especially designed to monitor behavioural data of patients suffering from mental illness, can in this way help clinicians monitor any unhealthy habits of patients with risk of developing cardiovascular disease.
Further, with the customisable action plans, each youth could follow “contingency plans” if they experience some symptoms related to their mental illness or if they have engaged in unhealthy activities. For example, a special trigger could set up if a youth has indulged in unhealthy food for several days in a row, or has had a low level of physical activity. The action plan listed for this trigger could then encourage individuals to engage in physical activities and and to try to avoid sugar and fat during the upcoming week.
References:
[1] Browser,D Medscape. Depression, Bipolar Disorder in Teens are CVD Risk Factors: AHA (2015, August 10) http://www.medscape.com/viewarticle/849312
[2] American Heart Association. Young people with mood disorders have increased risk of developing early cardiovascular disease (2015, August 11)
http://blog.heart.org/young-people-with-mood-disorders-have-increased-risk-of-developing-early-cardiovascular-disease/
[3] Walton, A Forbes. Teens with depression, bipolar disorder, should be screened for heart disease, experts say. (2015, August 11) http://www.forbes.com/sites/alicegwalton/2015/08/11/depressed-teens-may-be-at-higher-risk-for-heart-disease/
Goldstein BI, Carnethon MR, Matthews KA, et al. Major depressive disorder and bipolar disorder predispose youth to accelerated atherosclerosis and early cardiovascular disease. Circulation 2015.

Jun 13, 2016
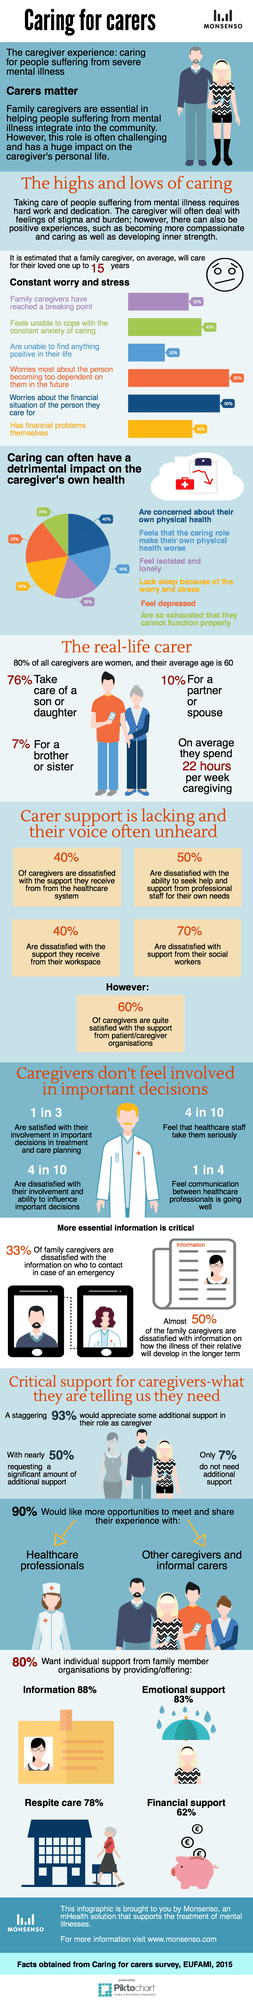
Family caregivers are essential in helping people suffering from mental illness integrate into the community. However, this role is often challenging and has a huge impact on the caregiver’s personal life.

May 30, 2016
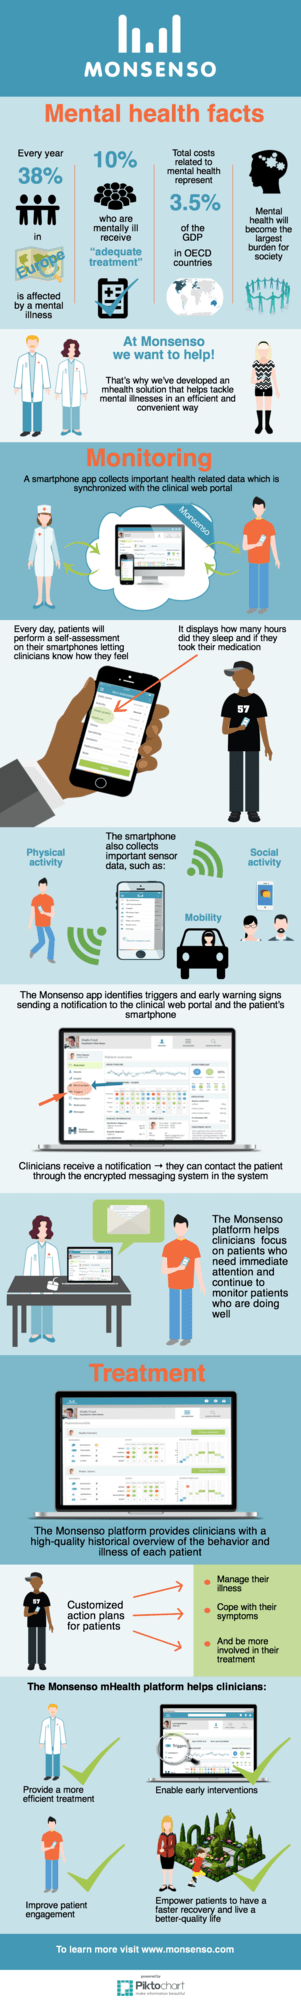
Monsenso, mHealth for mental health helps optimise the treatment of most major mental illnesses such as bipolar disorder, schizophrenia, borderline, depression, anxiety and PTSD.

May 24, 2016
In 2011, the European Union commissioned the Impact Consortium to write a report in regards to “The long-term mental health care for people with severe mental disorders.”
This blog post explores the principal issues involved in the long-term care of individuals suffering from severe mental systems mentioned in the report, and how some of these issues can be partially solved with the use of mobile health technology.
The long-term care of people suffering from severe mental disorders is one of the most significant challenges for the health care systems since the impact they have on individuals, families and societies is huge.
According to the report, schizophrenia has an estimated point prevalence of 0.4% and a lifetime risk of 1%, which means that 1 in every 100 people will suffer from schizophrenia during their lifetime. It is the 7th most important illness in terms of years lived with disability, accounting for 2.8% of disability caused by all illnesses. For people aged 15 to 44 years, it is the 3rd most important disease, accounting for 4.9% of disability resulting from all illnesses.
During the last few decades, the European Union has made a huge effort to overcome these barriers and to ensure high-quality longer-term care for people with severe mental disorders. These efforts started in the 60’s with the development of new pharmacological treatments for psychoses, which radically changed the prognosis of severe mental illness. In the 70’s and the 80’s, there was an emergence of new psychosocial interventions and new concepts of mental health care organisations [1].
Nowadays, there is a need to shift the health care model. The transition from traditional large psychiatric institutions to modern comprehensive community-based models of care, including acute patient units at general hospitals [1].
According to the report, this shift is necessary due to the following reasons:
- Accessibility to mental health care of people with longer-term mental disorders is much better with community-based services than with the traditional psychiatric hospitals
- Community-based services are associated with greater user satisfaction and increased met needs. They also promote better continuity of care making possible to identify and treat more often early relapses
- The community-based services protect the human rights of people with mental disorders and prevent stigmatisation of those people
- Studies comparing community-based services with other models of care consistently show significantly better outcomes on adherence to treatment [1]
However, European healthcare systems need to make lots of alterations if they want to provide accessible, effective, high-quality and long-term care to people suffering from severe mental disorders.
Challenges of the transition to new comprehensive community-based models of care
One of the main reasons why the development of long-term mental health services is insufficient is due to the lack of coordination between the different health services. A close coordination, and even joint funding and management of health and social care services is fundamental to cope with the new challenges European mental health systems are now facing. [1].
According to the report, these are the key principles to organise mental health services:
- Accessibility: Essential mental health care should be available locally, including outpatient and inpatient care, as well as rehabilitative care. Local services provide continuity of care in a satisfactory manner.
- Comprehensiveness: Mental health services should include all facilities and programmes required to meet the essential care needs of the populations.
- Coordination and continuity of care: People suffering from severe mental disorders often find it extremely difficult to gain access to various basic services; therefore, it is crucial that services work in a coordinated manner. This coordination should also include services that are not directly related to health, such as social services and housing services.
- Effectiveness: Service development should be guided by evidence of the effectiveness of particular interventions. For example, there is a growing evidence base of effective interventions for many mental disorders, among them depression, schizophrenia and alcohol dependence.
- Equity: A person’s access to services of good quality should be based on need. It is quite often that the people who need these type of services the most are the least able to ask for help.
- Respect for human rights: Services should respect the autonomy of persons with mental disorders, and encourage such persons to make decisions affecting their lives and treatment [1].
The solution
The Monsenso mobile health solution can facilitate five of the six points mentioned in the report to organise mental health services in an optimal way.
- Accessibility: With mobile technology and telehealth, care providers can reach patients living in remote locations at a minimal cost. These technologies offer care providers more flexibility to deliver health care while on-the-go or from different locations—expanding the clinic’s service offerings [2].
- Coordination and continuity of care: The Monsenso mobile health solution can facilitate and support the care of patients suffering from severe mental illnesses from community-based models. Due to its cloud-based model and unlimited scalability, patient records can be accessed by multiple organisations such as psychiatric institutions, general practitioners, and social services, among others.
- Effectiveness and equity: With help of the Monsenso smartphone app, care providers can identify on a daily basis triggers and early warning signs of all patients in the system. With the Monsenso mHealth solution clinicians can prioritize caring for individuals who need immediate attention and continue to monitor individuals who are stable. According to the National Institute of mental health, early intervention is critical to treating mental illness before it can cause tragic results such as serious impairment, unemployment, homelessness, poverty, and suicide [4].
- Respect for human rights: The Monsenso smartphone app enables patients to fill in daily self-assessments and write notes about how they feel. The information collected from these assessments is shared with the clinic, allowing individuals to be more involved with their treatment. The Monsenso smartphone app also provides individuals with customised action plans that act as guidelines in case their symptoms appear enabling individuals to take responsibility for their behaviours and actions.
References:
[1] The long-term mental health care for people with severe mental disorders. J.M Caldas de Almeida, H. Killaspy. Prepared under service contract with the Impact Consortium by the European Commission. 2011.
http://ec.europa.eu/health/mental_health/docs/healthcare_mental_disorders_en.pdf
[2] Increasing access to behavioural health care through technology. The U.S. Department of Health and Human Services Health Resources and Services Administration (2013, February).
http://www.hrsa.gov/publichealth/guidelines/behavioralhealth/behavioralhealthcareaccess.pdf
[3] Directors Blog: SAMHSA and NIMH partner to support early intervention for serious mental illness. P. Hyde and T. Insel. National Institute of Mental Health Blog (2014, June 17)
http://www.nimh.nih.gov/about/director/2014/samhsa-and-nimh-partner-to-support-early-intervention-for-serious-mental-illness.shtml
[4] Evidence based treatment for first episode of psychosis: Components of coordinated specialty care. PHD R. K. Heinssen. RAISE NIMH (2014, April 14).
http://www.nimh.nih.gov/health/topics/schizophrenia/raise/nimh-white-paper-csc-for-fep_147096.pdf
